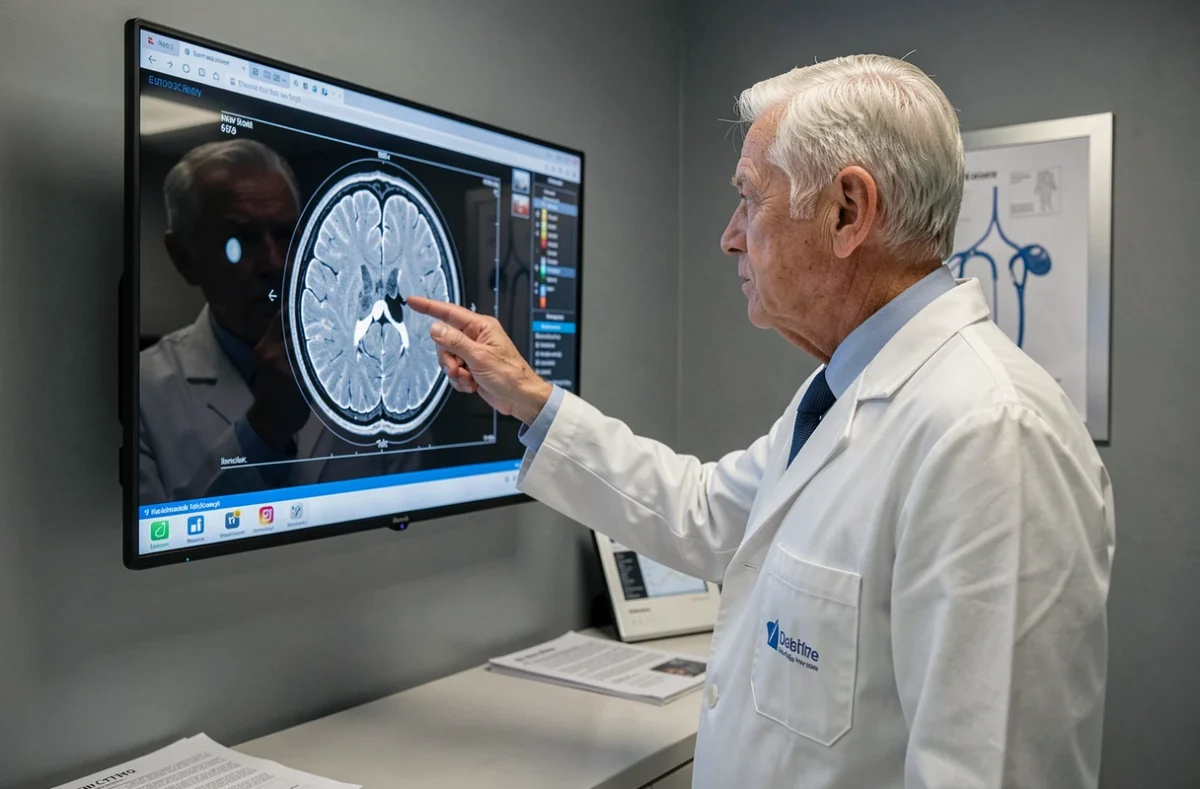
We receive an MRI report mentioning Fazekas 2 vascular leukopathy, and the first reaction is often to look up what this number corresponds to. Fazekas 2 leukopathy indicates the presence of confluent hyperintensities in the white matter, visible on the FLAIR sequences of the brain MRI. This intermediate grade on the Fazekas scale signals lesions that are more extensive than simple isolated spots, without reaching the most severe stage.
Fazekas 2 Score on MRI: What the Radiologist Actually Observes
The Fazekas score is a visual rating. The radiologist examines the FLAIR sequences and classifies the hyperintensities in the white matter according to their extent. At grade 2, the lesions are no longer small scattered points: they begin to coalesce, forming larger areas around the ventricles or in the deep white matter.
Understanding the factors of Fazekas 2 leukopathy allows for a better assessment of what is happening in the brain and guides prevention efforts.
A point often overlooked: the Fazekas score does not measure the exact volume of lesions. Two individuals classified as Fazekas 2 may have quite different actual lesion burdens. Longitudinal studies show that the increase in the volume of hyperintensities over time has been associated with cortical thinning in older adults, which the semi-quantitative score alone does not capture.
This is why an isolated Fazekas 2 result provides a partial picture. Comparing the current MRI to a previous examination is much more informative than a snapshot score, as it is the trajectory over time that informs about the progression dynamics.
Hypertension and Small Vessel Disease
Among the vascular risk factors, hypertension plays a central role in the genesis of white matter lesions. High blood pressure gradually damages the small cerebral arteries through a process called arteriolosclerosis. The walls of the arterioles thicken, their lumen narrows, and perfusion of the deep white matter decreases.
This chronic ischemia causes degradation of myelin (the protective sheath of nerve fibers) and axonal rarefaction. This is referred to as lipohyalinosis of small vessels, a mechanism that directly fuels the progression of hyperintensities visible on MRI.
Other Involved Vascular Risk Factors
Hypertension does not act alone. Several conditions accelerate small vessel disease:
- Type 2 diabetes alters cerebral microcirculation and promotes damage to the blood-brain barrier, amplifying white matter lesions
- Chronic smoking causes oxidative stress on the vascular endothelium, accelerating the aging of cerebral arterioles
- Dyslipidemias (notably excess LDL cholesterol) contribute to the thickening of arterial walls and reduction of cerebral blood flow
- Atrial fibrillation and other cardiac rhythm disorders reduce the quality of cerebral perfusion over time
The accumulation of these factors multiplies the risk of progression to a more advanced stage. Acting on blood pressure remains the most documented lever to slow the evolution of lesions, but the target level should be discussed on a case-by-case basis with a physician, particularly considering age and fall risk.
Cognitive and Neurological Consequences of Fazekas 2 Stage
At Fazekas 2 stage, symptoms may remain subtle or manifest as progressive functional disorders. White matter lesions disrupt connections between different regions of the brain, which explains the nature of the difficulties encountered.
Frequently Reported Cognitive Disorders
The slowing of information processing speed is often the first sign detected. It takes longer to react, to follow a fast conversation, or to manage multiple tasks simultaneously. Executive functions (planning, organization, mental flexibility) are affected before pure memory.
This cognitive profile differs from that of Alzheimer’s disease, where episodic memory disorders dominate from the outset. In Fazekas 2 vascular leukopathy, it is rather the overall efficiency that declines: difficulties in organizing, increased cognitive fatigue, and the need for more time to complete routine tasks.
Associated Neurological Risks
Confluent lesions in the white matter increase the risk of gait and balance disorders. The deep white matter contains the motor fibers connecting the cortex to subcortical structures, and their alteration can lead to a shuffling gait or postural instability.
The risk of vascular dementia increases as lesions progress over time. Fazekas 2 leukopathy does not mean that dementia is inevitable, but it serves as a warning signal that justifies regular neurological follow-up.

MRI Monitoring and Daily Prevention Levers
A Fazekas 2 score calls for structured follow-up rather than passive concern. Comparing two MRIs spaced twelve to twenty-four months apart allows for assessing whether the lesions remain stable or progress. This trajectory guides therapeutic decisions much more than a fixed score.
The markers of small vessel disease are not limited to hyperintensities. The radiologist also looks for lacunes (small silent infarcts), microbleeds, and dilation of perivascular spaces. All of these MRI signs create a more complete picture than the Fazekas score alone.
In terms of prevention, controlling blood pressure, engaging in regular age-appropriate physical activity, and managing diabetes or dyslipidemias are the levers on which we can concretely act. Each corrected risk factor reduces the vascular burden on the small cerebral arteries.
The dialogue with the neurologist or primary care physician remains the starting point for adapting the prevention strategy to each situation. A stable Fazekas 2 over several years does not have the same significance as a Fazekas 2 that has rapidly evolved since a previous normal examination. It is this dynamic reading that gives the score its true clinical relevance.


